Radiology Practice Setup: Credentialing, Billing, and Revenue Cycle Essential
The clinical and equipment side of opening a radiology practice gets most of the attention, but credentialing, payer enrollment, billing, and revenue cycle infrastructure determine whether that investment actually generates revenue from day one. This guide walks through the administrative foundation every new Maryland radiology practice needs to build before, and immediately after, opening its doors.

Setting Up the Administrative Foundation for a Radiology Practice
A new radiology practice can have the right equipment, the right location, and the right referral relationships, and still struggle financially in its first year if the administrative foundation underneath it isn't built correctly. Credentialing, payer enrollment, billing infrastructure, and revenue cycle workflow don't get the same attention as equipment selection during practice planning, but they're what actually determine whether the clinical and capital investment translates into collected revenue on any predictable timeline.
For radiology practices and imaging centers launching across Maryland, whether a hospital-affiliated group in Baltimore or an independent center in Rockville, Columbia, or Frederick, this administrative foundation needs to be in place before the first patient is scanned, not built reactively once claims start getting denied. This guide walks through exactly what that foundation involves.
Radiology Credentialing and Provider Enrollment
Credentialing establishes that each interpreting radiologist is properly identified and authorized to bill for services, and it starts with the same core elements every specialty requires: an accurate NPI and taxonomy code designation, a complete and current CAQH profile, and state licensure confirmed and active. Radiology adds a layer most specialties don't deal with, since enrollment needs to correctly reflect whether a radiologist bills individually, through a group, or under a specific facility relationship.
This distinction matters practically. A radiologist joining a group that reads studies for a hospital in Towson needs enrollment reflecting that group relationship accurately. A radiologist billing independently for professional component interpretation at an imaging center in Salisbury needs enrollment that separately and correctly identifies that distinct arrangement. Getting this wrong doesn't just delay credentialing, it can misattribute claims once billing actually begins.
Credentialing timelines vary by payer, and radiology practices adding multiple interpreting physicians at launch, common for larger groups covering several Maryland locations, should expect this process to take genuine weeks to months per provider, not a quick formality completed alongside hiring paperwork.

Payer Enrollment and Payer Contracting
Once credentialing is underway, payer enrollment runs on its own parallel track. Medicare enrollment through PECOS, Maryland Medicaid enrollment, and individual commercial payer applications each carry distinct timelines, requirements, and, in Maryland's case, connection to the state's HealthChoice managed care structure for Medicaid patients specifically.
Payer contracting for radiology carries specific negotiation considerations beyond standard rate discussions. Since most imaging CPT codes split payment between professional and technical components, contract terms should clearly address how each component is reimbursed, particularly for practices in a split-billing arrangement where a facility bills the technical component while an independent radiology group bills separately for interpretation. Practices operating across multiple counties, from Howard County to Anne Arundel County to Frederick County, need contracting clarity on whether enrollment and negotiated rates apply uniformly across every location or require separate confirmation at each site.
Setting Up Radiology Billing
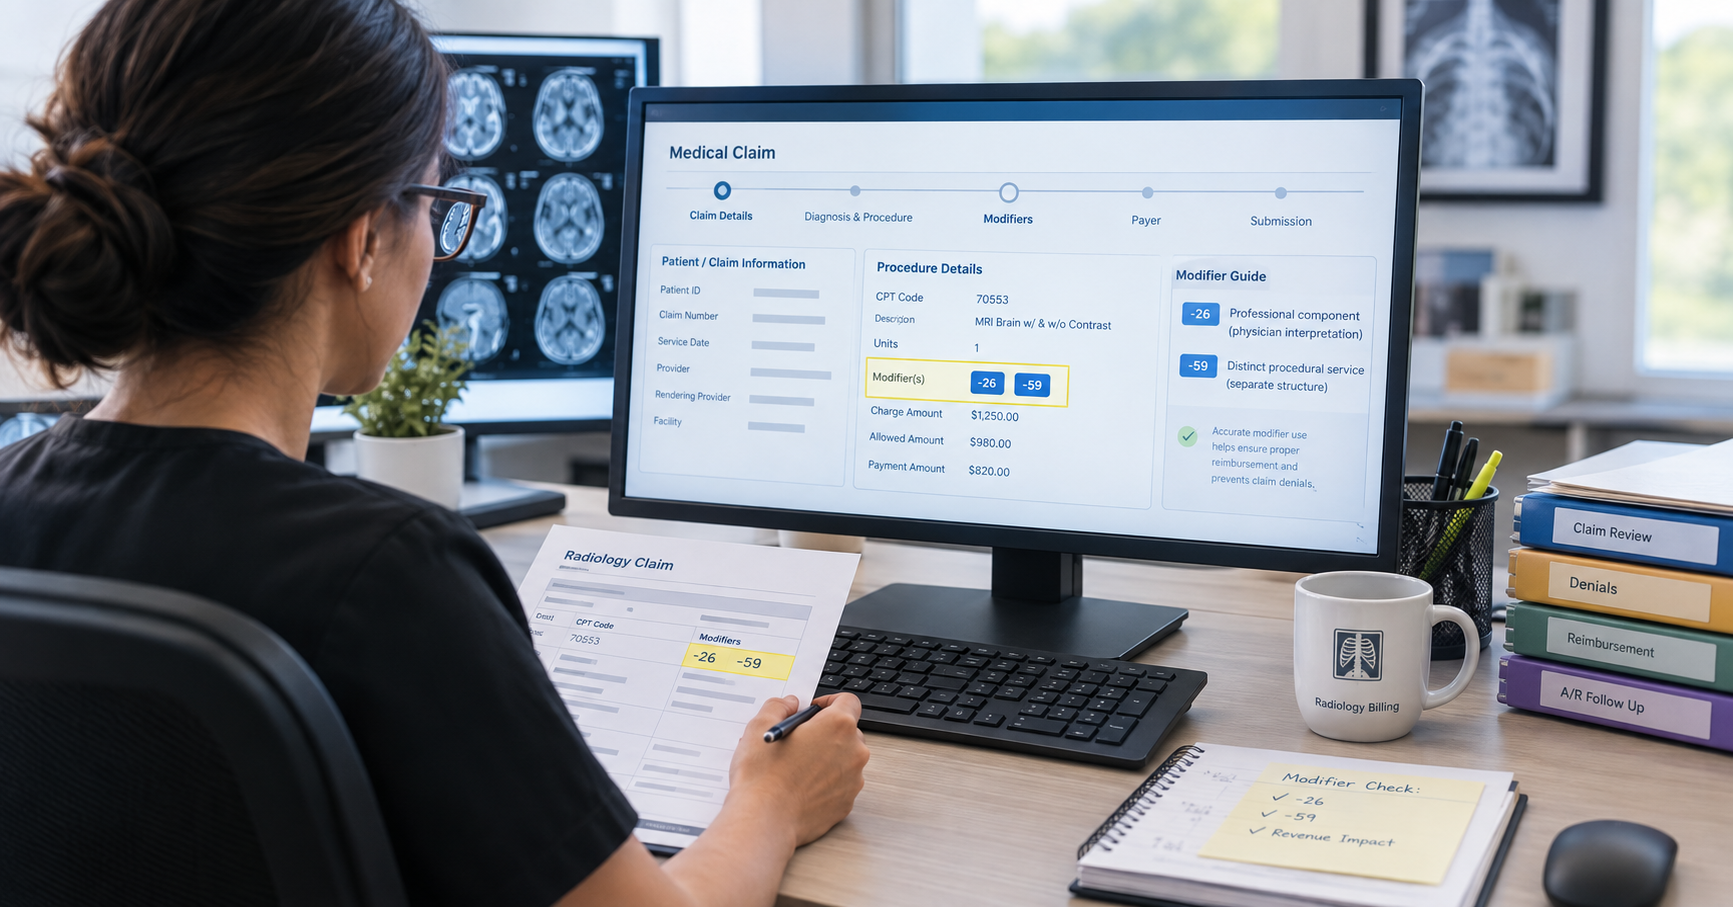
Radiology billing infrastructure needs to be built around the specialty's core structural reality: most services split into a technical component, covering equipment, staffing, and facility costs, and a professional component, covering the radiologist's interpretation and signed report. Modifier 26 identifies the professional component, modifier TC identifies the technical component, and global billing with no modifier applies only when the same entity provides both.
Setting this up correctly from the start means confirming, for every service the practice will offer, exactly which billing scenario applies based on actual equipment ownership and staffing arrangements. A practice in Bethesda contracting out interpretation to an outside radiology group needs its billing system configured for split TC billing from day one, not retrofitted after the first batch of claims comes back denied for a mismatch between what was billed and what the ownership arrangement actually supports.
Insurance Eligibility and Authorization Workflows
Eligibility verification needs to happen close to the actual date of imaging service, not just at the point of scheduling, since coverage can change in the interim. This matters more in radiology than in many specialties because imaging is frequently scheduled separately from the ordering visit, creating a real gap where coverage status can shift.
Prior authorization adds another layer specific to advanced imaging. MRI, CT with contrast, PET, and similar studies are reviewed far more often than plain X-rays, and that review frequently routes through a radiology benefit manager, eviCore and Carelon among the larger organizations handling this on behalf of many commercial and Medicare Advantage plans, rather than the payer directly. A new practice in Annapolis or Glen Burnie building its authorization workflow needs to account for this routing explicitly, since assuming every payer's authorization process works the same way is a common, avoidable source of early denials.

Building a Radiology Claims Management Process
A dependable claims management process confirms, before submission, that the correct modifier reflects the actual billing scenario, that authorization on file matches the specific CPT code performed, and that documentation, specifically the signed interpretation report for professional component claims, is complete. Claims should be reviewed for these specific radiology risk points before submission, rather than relying solely on post-denial correction.
For practices launching with multiple interpreting radiologists or multiple locations, a standardized claims review checklist applied consistently, whether the study was performed in Baltimore or Hagerstown, prevents the kind of site-by-site inconsistency that otherwise creeps in as a practice scales.
Radiology Revenue Cycle Management
Revenue cycle management in radiology connects every piece already discussed into one continuous system: credentialing accuracy feeding into correct claim attribution, eligibility and authorization confirmed before service, accurate modifier and coding decisions, clean claim submission, disciplined payment posting, active accounts receivable monitoring, and denial management that traces problems to their root cause.
New practices across Maryland benefit from establishing revenue cycle reporting from the very first claims submitted, tracking clean claim rate, denial rate by category, and days in accounts receivable from launch rather than waiting months to establish a baseline. A practice in Columbia or Ellicott City that starts tracking these metrics immediately can catch a workflow gap in week three instead of discovering it as a mounting accounts receivable problem in month six.

Common Billing and Credentialing Problems New Radiology Practices Face
- Beginning operations before payer enrollment is genuinely active, not merely submitted, resulting in an early batch of unbillable services.
- Misconfigured modifier logic at billing system setup, applying global billing or the wrong component modifier given the practice's actual ownership and staffing arrangement.
- Incomplete understanding of radiology benefit manager routing, assuming a single authorization process applies universally across all payers.
- Inconsistent credentialing across multiple locations, particularly for groups expanding quickly across several Maryland counties without standardizing the enrollment process at each site.
- Delayed revenue cycle reporting, not establishing denial and claims tracking until a problem has already compounded across months of claims.
How to Build an Efficient Radiology Revenue Cycle From the Start
- Begin credentialing and payer enrollment as early as possible, well before the planned opening date, given how genuinely long the process takes per provider and per payer.
- Configure billing systems around the practice's actual, specific ownership and staffing arrangement for every service offered, rather than a generic default.
- Build authorization workflows that account for radiology benefit manager routing explicitly, confirming which organization reviews which payer's requests.
- Establish standardized claims review checklists applied consistently across every practice location.
- Track clean claim rate, denial rate by category, and days in accounts receivable from the very first claims submitted, not after a problem has already emerged.
- Review payer contracts periodically as the practice grows, confirming rates and terms still reflect current volume and negotiating position.
Frequently Asked Questions
What credentialing does a new radiology practice need to complete?
Accurate NPI and taxonomy designation for every interpreting radiologist, a complete CAQH profile, active state licensure, and enrollment correctly reflecting whether each radiologist bills individually, through a group, or under a specific facility relationship.
How long does radiology credentialing typically take?
Timelines vary by payer, but the process genuinely takes weeks to months per provider, which is why credentialing should begin well before a practice's planned opening date rather than alongside final hiring steps.
What makes radiology billing different from other specialties?
Most imaging CPT codes split payment between a technical component, covering equipment and facility costs, and a professional component, covering the radiologist's interpretation, billed with modifier TC and modifier 26 respectively, or globally when one entity provides both.
Why does prior authorization matter so much for a new radiology practice?
Advanced imaging, MRI, CT with contrast, and PET among them, is reviewed far more often than plain X-rays, and that review frequently routes through a radiology benefit manager rather than the payer directly, requiring a workflow built around that specific routing structure.
What revenue cycle metrics should a new radiology practice track from launch?
Clean claim rate, denial rate broken down by category, and days in accounts receivable, established from the very first claims submitted rather than after a revenue problem has already developed.
What is the most common credentialing mistake new radiology practices make?
Beginning operations before payer enrollment is genuinely active, submitting an application is not the same as being enrolled, which results in an early batch of services that can't actually be billed.
Conclusion
The administrative foundation of a radiology practice, credentialing, payer enrollment, billing configuration, and revenue cycle infrastructure, determines how quickly clinical and equipment investment actually converts into collected revenue. For practices launching across Maryland, from Baltimore and Bethesda to Columbia, Frederick, and Salisbury, building this foundation deliberately before opening, rather than assembling it reactively once claims start moving, is what separates a smooth first year from months of avoidable revenue delay.
Edge RCM CTA
Getting credentialing, payer enrollment, and billing infrastructure right before a radiology practice opens protects the revenue behind every study performed from day one. Edge RCM, based in Reisterstown, supports new and growing radiology practices across Maryland with credentialing, payer enrollment, medical billing, and revenue cycle setup built specifically around radiology's professional and technical component billing structure.