Modifier 26 vs TC in Radiology Billing: What Practices Need to Know
Modifier 26 and modifier TC determine how radiology revenue splits between the physician's interpretation and the facility's technical work. This guide covers exactly what each modifier means, whether they can ever be billed together, documentation requirements, and how Maryland imaging centers and radiology practices can build a review process that protects revenue already earned.
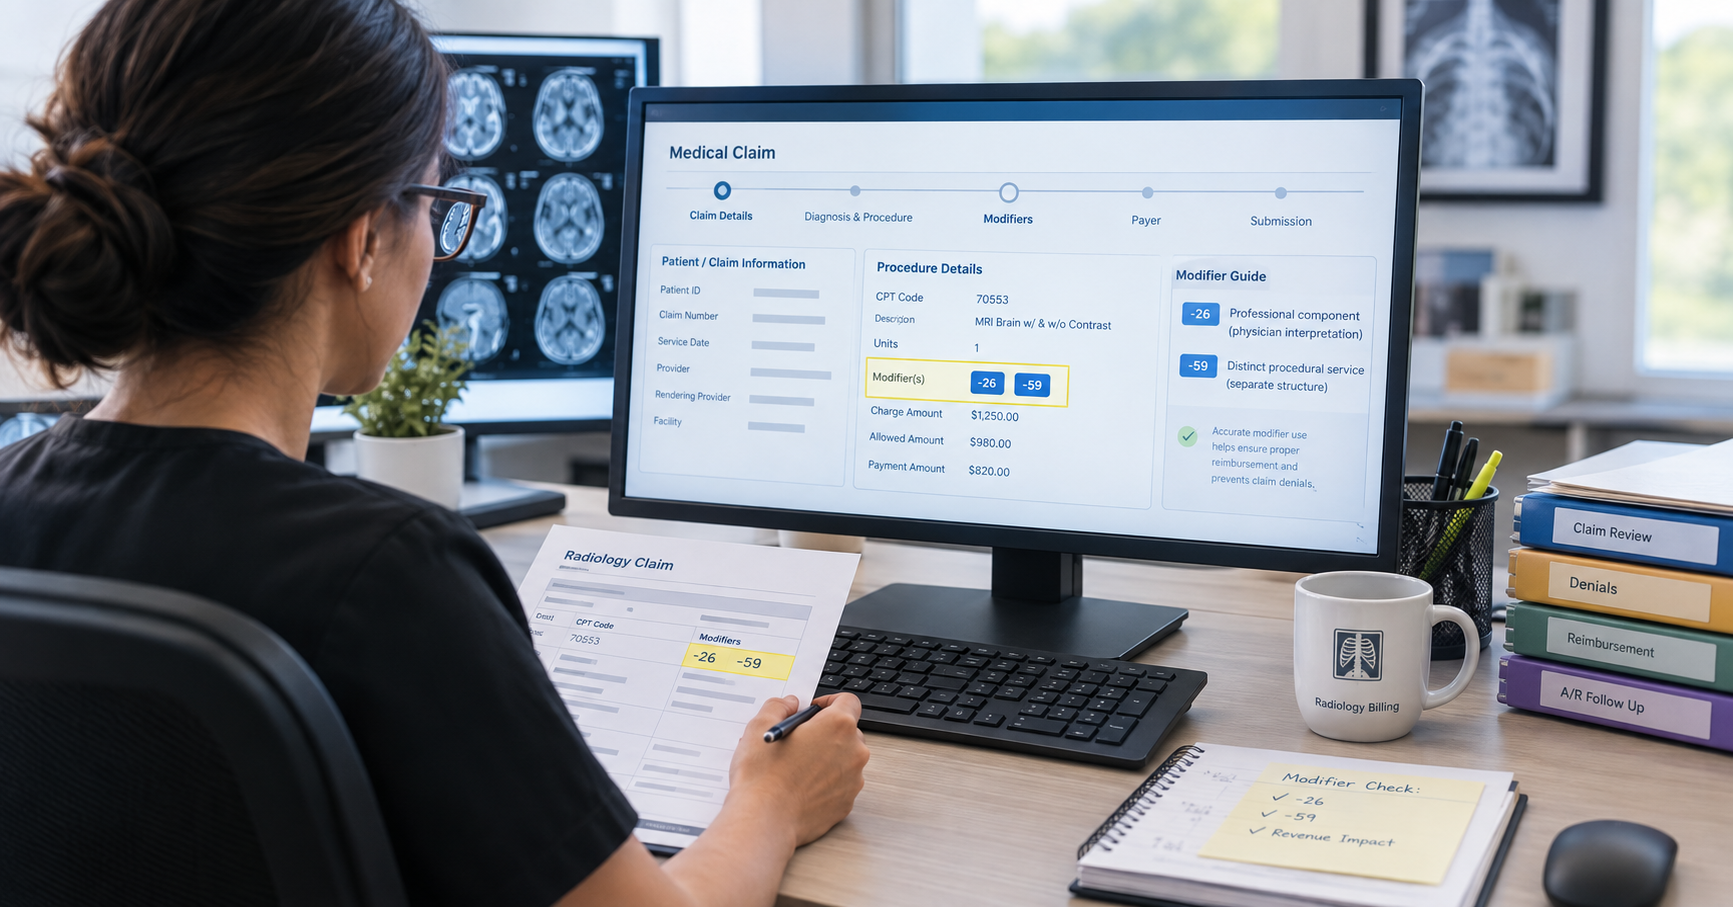
Radiology revenue depends on getting a distinction right that has nothing to do with clinical accuracy and everything to do with billing structure: who owns the equipment, and who interpreted the study. Most radiology medical billing runs through two modifiers built specifically to reflect that distinction, modifier 26 for the professional component and modifier TC for the technical component, and confusion between them is one of the more consistent, avoidable sources of denied and underpaid claims across medical imaging centers.
For advanced radiology practices and imaging centers throughout Maryland, from hospital-based groups in Baltimore to independent centers in Rockville and Frederick, this isn't a minor coding detail. It's a direct driver of how much of the radiology revenue already earned through clinical work actually reaches the practice. This guide covers exactly what each modifier means, a question that comes up constantly, whether both can ever be billed together, and the practical steps that protect revenue from avoidable modifier errors.
What Modifier 26 Means: The Professional Component
Modifier 26 is defined as the professional component of a radiology service. It's used to report the physician's work specifically, interpreting the imaging study and producing the formal written report, separate from any equipment, staffing, or facility cost involved in performing the study itself. Modifier -26 applies when a radiologist interpreted the results and signed a formal report, but didn't own the imaging equipment or employ the technologist who actually performed the study.
This is the piece of radiology billing tied directly to clinical judgment. A radiologist reading studies for a hospital in Towson or Salisbury, without being employed by that hospital and without owning any of its imaging equipment, bills modifier 26 specifically for that interpretive work.
What Modifier TC Means: The Technical Component
Modifier TC identifies the technical component, the equipment, supplies, technologist labor, and facility overhead required to actually produce the image. Whichever entity owns the equipment and employs the staff performing the study, commonly a hospital, an independent imaging center, or a freestanding radiology clinic, bills modifier TC for that portion.
There's no physician interpretive work reflected in a TC claim at all. It exists purely to capture the cost of running the equipment and facility that made the study possible in the first place.
Can Modifier 26 and TC Be Billed Together?
This is one of the most common points of confusion in radiology medical billing, and it deserves a direct answer: no, modifier 26 and modifier TC are not billed together on the same claim line for the same performed service. They represent two separate, mutually exclusive billing scenarios, not two add-ons meant to be combined.
Here's why that confusion happens. A single imaging study can generate two separate claims from two separate entities, the facility bills modifier TC for its portion, and the interpreting radiologist, or their separate billing group, bills modifier 26 for the interpretation. Two claims exist, but neither claim carries both modifiers at once. If the same entity owns the equipment and performs the interpretation, no modifier is used at all, the service is billed globally as a single combined claim instead. Appending both modifiers to a single line, or billing globally while a separate entity also bills a component modifier for the same study, creates a duplicate billing conflict that payers are specifically built to catch.

Global Billing: When Neither Modifier Applies
Global billing applies when one entity provides both the technical and professional components of a study, owning the equipment, employing the technologist, and personally interpreting the images. In this scenario, no modifier is appended at all, and the full combined payment goes to that single billing entity. This is common among private radiology practices and medical imaging centers across Maryland that own their own equipment and staff their own interpreting radiologists directly, rather than contracting interpretation out to a separate group.
Documentation Requirements for Modifier 26
Billing modifier 26 correctly depends on documentation that actually supports it. The interpreting provider needs to have personally reviewed the study and produced a signed, formal interpretation report, not a preliminary read or an informal consultation. That report needs to be complete, dated, and attributable specifically to the billing provider, since payers reviewing a modifier 26 claim are confirming that genuine, documented interpretive work occurred, not simply that a radiologist happened to be affiliated with the case in some way.
Incomplete or unsigned reports are a recurring, avoidable reason modifier 26 claims get denied even when the interpretation itself was performed appropriately.

How Modifier Selection Directly Affects Radiology Revenue
Because most imaging CPT codes split total payment between the technical and professional components based on that code's specific relative value unit allocation, modifier accuracy isn't a technicality, it's the mechanism that actually determines how radiology revenue gets distributed. Billing globally for a service that was actually only the professional component overstates the claim. Billing modifier TC for a code that doesn't carry an applicable technical component in the current fee schedule results in denial. And inconsistent modifier habits across a growing imaging center, with multiple sites across Columbia, Bel Air, and Gaithersburg, for example, can quietly compound into a meaningful, recurring revenue gap across hundreds of monthly claims.

Common Errors That Cost Imaging Centers Revenue
- Billing globally for interpretation-only work , when the practice didn't actually own the equipment used to perform the study.
- Assuming modifier 26 and TC can be combined on a single claim, rather than understanding they represent separate billing scenarios entirely.
- Submitting modifier 26 without a complete, signed interpretation report to support it.
- Applying modifier TC to a CPT code that doesn't carry a separately billable technical component in the current year's Medicare Physician Fee Schedule.
- Inconsistent modifier practices across multiple locations, particularly relevant for radiology groups operating across several Maryland counties with different ownership arrangements at each site.

Real Billing Examples Across Maryland Practice Settings
Hospital-based interpretation, Baltimore
A hospital in Baltimore owns its imaging equipment and employs its technologists, but contracts with an independent radiology group for interpretation. The hospital bills the technical component with modifier TC. The independent radiology group bills the professional component with modifier 26 for the same study, on a separate claim.
Independent imaging center, Rockville
A freestanding imaging center in Rockville performs the technical work and bills modifier TC, while contracting interpretation out to a radiology group that bills modifier 26 separately, functioning under the same split-billing structure as the hospital example above.
Vertically integrated private practice, Frederick
A radiology practice in Frederick owns its own imaging equipment and employs its own interpreting radiologists directly. Since one entity provides both components, the practice bills globally, with no modifier at all.
Building a Modifier Review Process to Protect Radiology Revenue
A dependable review process confirms ownership and employment status for every billing site before claims go out, verifies that modifier 26 claims are backed by a complete, signed interpretation report, checks current-year PC/TC indicators for each CPT code rather than assuming they're unchanged from the prior year, and tracks denial patterns specifically tied to modifier selection so recurring errors get corrected at the workflow level rather than claim by claim. Radiology groups and medical imaging centers operating across multiple Maryland communities benefit from standardizing this review across every location, rather than allowing modifier practices to vary informally site by site.
Frequently Asked Questions
What does modifier 26 mean in radiology billing?
Modifier 26 identifies the professional component of a radiology service, the physician's interpretation and signed, formal report, billed when the interpreting provider doesn't own the equipment or employ the staff who performed the study.
What does modifier TC mean?
Modifier TC identifies the technical component, the equipment, supplies, staffing, and facility costs of performing the study, billed by whichever entity owns the equipment and employs the technologist.
Can modifier 26 and modifier TC be billed together?
No. They represent separate, mutually exclusive billing scenarios. A single study may generate two separate claims from two different entities, one with modifier TC and one with modifier 26, but neither individual claim carries both modifiers at once, and no modifier is used at all when one entity bills globally for both components.
What documentation supports a modifier 26 claim?
A complete, signed, formal interpretation report specifically attributable to the billing provider, confirming that genuine interpretive work was actually performed, not just a general affiliation with the case.
When should a practice bill globally instead of using either modifier?
When the same entity owns the imaging equipment, employs the technologist, and performs the interpretation, meaning all components of the service came from one billing entity.
Why do modifier errors matter for radiology revenue specifically?
Because CPT codes split payment between technical and professional components based on each code's individual relative value unit allocation, incorrect modifier selection can result in denied claims, duplicate billing conflicts, or claims that don't reflect the actual value of the work performed.
Conclusion
Modifier 26 and modifier TC exist to answer one specific question for every imaging study: who did what. Getting that answer right, and understanding clearly that the two modifiers represent separate scenarios rather than something billed together, is foundational to protecting radiology revenue across every claim an imaging center or radiology group submits. For practices throughout Maryland, from Baltimore's hospital-based radiology groups to independent medical imaging centers in Frederick, Rockville, and beyond, building a consistent modifier review process is what turns accurate clinical work into accurately collected revenue.
Edge RCM CTA
Modifier 26 and TC errors are a direct, measurable drain on radiology revenue, and they're also among the most preventable billing mistakes once a practice has a reliable review process in place. Edge RCM, based in Reisterstown, supports radiology practices and medical imaging centers across Maryland with coding accuracy review, claims management, and denial prevention built specifically around professional and technical component billing.